
An owner can have every report the software produces and still misread their practice metrics. Most owners look at one number, usually revenue, or they fixate on a single metric without knowing how to interpret it. The reports are not the problem. Reading them is.
At a large group there is a person whose whole job is to read those numbers every day, whether the title is operations leader, operations manager, or director of operations. Most independent practices do not have that person, so the practice metrics sit there looking fine while the real story goes unread. Here are the three metrics owners misread most, and why each one fools you until you read it against the number beside it.
What does it mean to read your practice metrics?
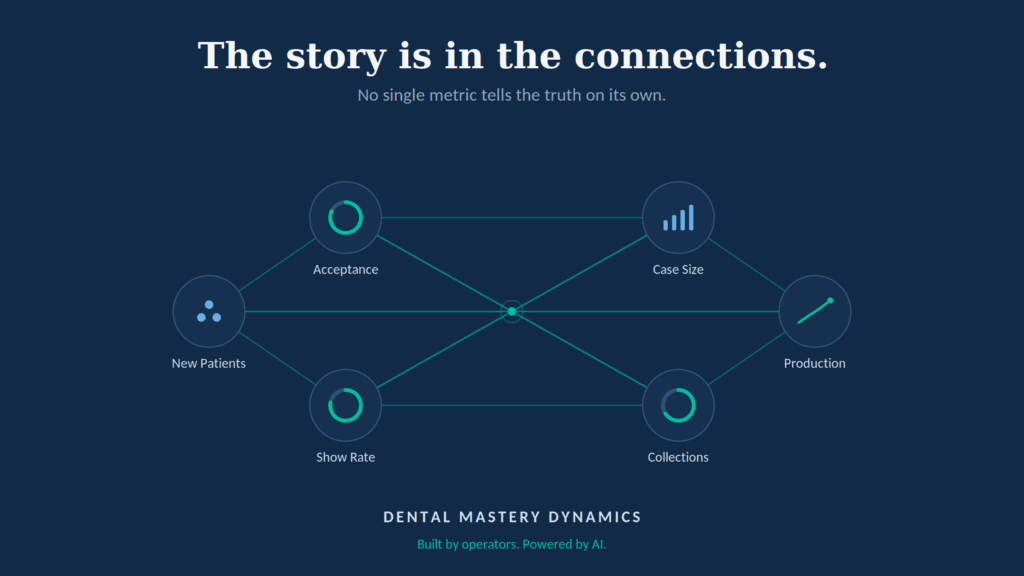
Reading your practice metrics means looking at numbers in context and in pairs, not staring at one figure in isolation. A single number rarely tells the truth on its own, because the story is in how it relates to the numbers around it.
An operations leader does this without thinking about it. They never look at acceptance without also asking what was accepted, and they never celebrate production without checking what was collected. That habit of reading practice metrics in pairs is the whole skill, and it is the one most owners were never taught, because they were trained to be clinicians, not analysts. The good news is that the pairs are learnable, and we cover the core ones in the three KPIs that control profitability.
Why is case acceptance the most misleading number in your practice?
Because acceptance percentage tells you how much of what was presented got accepted, and nothing about how much was presented. A hundred percent acceptance of two thousand dollars in treatment is a completely different practice than a hundred percent acceptance of a hundred dollars, and the percentage looks identical on the screen.
This is the first of the three, and the one owners are proudest of. We have ninety percent acceptance. We have a hundred percent. Every patient gets what I recommend. That is worth being proud of, and the question underneath it is what they are accepting. Comprehensive treatment, or only the chief complaint, with the practice quietly counting on them coming back for the rest?
I sat with a practice recently that believed half of its limited-exam patients came back for a comprehensive exam. When I asked leadership, the real number was closer to twenty percent. In the day-to-day, limited and comprehensive exams were not being separated, so it all read as accepted and the acceptance percentage stayed beautiful.
Meanwhile, the practice was booking revenue, in its own mind, that four out of five of those patients were never going to come back and complete. The number was not lying. It was answering a different question than the one the owner thought they were asking. Read acceptance next to average case size, and the picture changes. This is also why presentation depth and the SIR method matter so much, because they move the case size, not the percentage.
Why doesn’t your bank account match your production?
Because production is what you diagnosed and scheduled, and collections are what actually landed in the bank, and those are not the same number. A practice can post outstanding production and still wonder why the account does not reflect it, because the collections never followed the production out the door.
This is the second metric owners misread, because production read by itself feels like success, and it is only half the story. The other half is whether the money was collected, and the gap between the two is where a lot of practices lose a result they thought they had already earned. Acceptance and collections work together. Strong acceptance with weak collections is a practice that looks healthy on the production report and feels broke at the bank, and the owner cannot understand why until someone reads the two numbers side by side.
Why is your new patient count misleading on its own?
Because a rising new patient count looks like growth even when you are not converting the patients you already have. Read on its own it feels like the answer to everything, which is exactly what makes it the easiest number to chase in the wrong direction. Fix what you already have first. New patient demand matters, and it is rarely the first lever to pull when you are not executing on the patients already in the chair.
New patient count is the third metric owners misread, and the one they chase hardest, because it feels like the answer to everything. The instinct is that if you throw more at the wall, more will stick. There is some truth to that, and it falls apart when you are converting half of what you already have. More new patients poured into a practice that does not execute on the patients in front of it is more water into a leaky bucket. The cheaper, faster growth is almost always in the patients you already paid to attract, which is the whole point of growing revenue without adding new patients.
How do you read your practice metrics without an operations leader?
You start by reading your practice metrics in pairs instead of one at a time. Acceptance next to average case size, production next to collections, and new patient demand only after you have looked at how well you execute on the patients you already have.
- Acceptance with case size. A high percentage on small cases is not the win it looks like.
- Production with collections. The bank reflects what you collected, not what you produced.
- Demand with execution. Chase new patients after you are converting the ones you have, not before.
Underneath all three pairs is the same truth: a practice comes down to two numbers, revenue and deposits. Almost every metric is a clue about one of those two, and reading them in pairs is how you turn a screen full of figures into a decision.
Here is the honest part. Reading these pairs once is easy. Reading them every single morning, consistently, and acting on what they say, is a job. It is the job an operations leader does at a larger group, and it is the job most independent practices have no one to do. That is exactly the gap Dental Mastery Dynamics was built to fill. The Dental Coach AI reads your practice metrics every morning, in context, and tells your team what the story actually is, the read of an operations leader without the six-figure hire. If that is the seat your practice has been missing, take a look at our solutions and pricing.
Frequently Asked Questions
What is the most misread number in a dental practice?
Case acceptance percentage. It tells you how much of what was presented got accepted, and nothing about how much was presented, so a high percentage on small cases looks identical to a high percentage on comprehensive ones. Read it next to average case size to see the real picture.
What is the difference between production and collections?
Production is what you diagnosed and scheduled. Collections are what actually landed in the bank. Your account reflects collections, not production, which is why a practice can post strong production and still feel short on cash.
Should I focus on new patients or my current schedule?
Your current schedule first. If you are converting only part of the patients you already have, adding new patients pours more demand into the same leak. Fix execution, then drive demand.
How do I read practice metrics without an operations leader?
Read the numbers in pairs rather than one at a time: acceptance with case size, production with collections, and demand with execution. The harder part is doing it every day, which is the work an operations leader, or a tool built to act like one, handles for you.
Can AI read my practice metrics for me?
Yes, when it is connected to your practice management system. The Dental Coach AI reads your practice metrics every morning, in context, and tells your team what the story is, which is the daily read most independent practices do not have anyone on staff to do.